
In February 2018, a team led by Yuliang Zhao, Baoquan Ding, Guangjun Nie and Hao Yan reported in Nature Biotechnology that a folded DNA structure, injected into the bloodstream of tumour-bearing mice, had opened inside tumour blood vessels and released the clotting enzyme thrombin. As a result, the tumours’ blood supply clotted and their growth slowed. The team also tested the structure for safety in Bama miniature pigs. It was one of the clearest demonstrations that nanorobots for drug delivery could do something useful in a living animal. More than eight years later, as of 17 October 2026, we couldn’t find a registered human trial of that system, or of any comparable nanorobotic drug carrier. This article looks at what separates a nanoscale machine that delivers a payload in a mouse from a drug-delivery technology a regulator would let near a patient.
Key Takeaways
- “Nanorobot” covers very different things. People apply it to DNA origami containers, enzyme-powered particles and magnet-steered capsules. However, they share little beyond size and a sense of motion.
- The strongest results are still in animals. DNA nanorobots have caused tumour clotting in mice, enzyme-driven nanobots have shrunk mouse bladder tumours by about 90%, and researchers have steered magnetic microrobots through pig and sheep vasculature.
- We found no human trial. As of 17 October 2026, we found no registered or reported human trial of a nanorobotic or microrobotic drug-delivery system. Direct registry queries were unavailable, so this rests on searches of registry and literature content.
- Approved nanomedicines aren’t robots. Liposomes and lipid nanoparticles are passive carriers, so their approvals don’t count as evidence that nanorobots work in people.
- The hard problems come after the demonstration. Manufacturing, dose, clearance and control in a human-sized body decide whether a system can reach the clinic, and those are the problems current studies mostly leave open.
Quick Navigation
- What counts as a nanorobot for drug delivery?
- How nanorobots for drug delivery actually release a drug
- Four nanorobotic drug delivery studies and what they showed
- Nanorobots for drug delivery in clinical trials: the evidence
- The engineering problems animal studies cannot settle
- What a credible path to clinical use looks like
- Where nanorobotic drug delivery could make a difference
- The next milestone worth watching
- What the evidence lets us say
- Frequently asked questions
- What are nanorobots for drug delivery?
- Are nanorobots currently used to deliver drugs to human patients?
- What is the difference between a nanorobot and a nanoparticle?
- How do nanorobots navigate through the body?
- What safety and manufacturing challenges remain?
- When could nanorobotic drug delivery become clinically available?
What counts as a nanorobot for drug delivery?
There’s no agreed definition, and that’s the first problem. In the research literature, “nanorobot” is used for systems that sense, move, or change shape in response to a signal. Journalists and companies use it for almost anything small that carries a drug. The difference matters, because evidence for one category says little about another.
Table: scroll sideways to view all columns when needed.
| Category | Example | Moves itself? | Externally controlled? | Responds to a target? | Size |
|---|---|---|---|---|---|
| DNA nanostructure (“DNA nanorobot”) | Thrombin-loaded DNA origami (Li et al., 2018) | No; carried by blood flow | No | Yes; opens on binding a tumour marker | Tens of nanometres |
| Catalytic nanomotor (“nanobot”) | Urease-coated silica particles (Simó et al., 2024) | Yes; propelled by an enzyme reaction with urea | No | Indirectly, by mixing and penetrating tissue | Hundreds of nanometres |
| Magnetic microrobot | Gel capsule with iron oxide (Landers et al., 2025) | No | Yes; magnetic fields steer it | No; an operator aims it | Largest of the four; sized to fit target vessels |
| Conventional nanoparticle carrier | Liposomes, lipid nanoparticles | No | No | Sometimes, via surface ligands | Tens to hundreds of nanometres |
The last row is the important comparison. Liposomal doxorubicin and the lipid nanoparticles in mRNA vaccines are approved, widely used nanomedicines. They don’t move under their own power, can’t be steered, and don’t change state in a controlled way. Calling them nanorobots would blur the line this article is trying to draw. Their approvals show that nanoscale carriers can be manufactured and regulated. They show nothing about whether a self-propelled or steerable machine can be.
Scale is the other confusion. Some of the most clinically advanced “nanorobots” are really microrobots, large enough to see on an X-ray and to steer with magnets, but too large to pass through capillaries.
How nanorobots for drug delivery actually release a drug
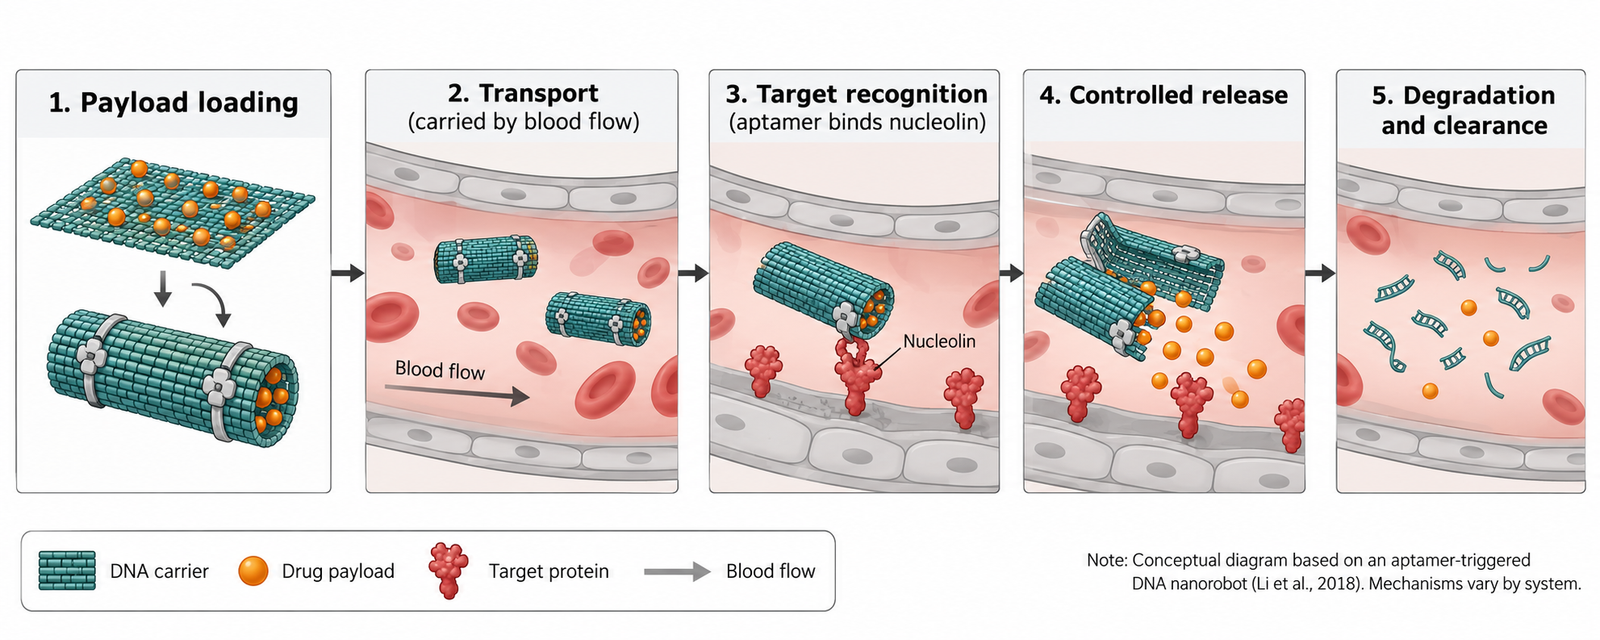
It helps to break drug delivery into separate jobs: loading the drug, moving it, finding the target, releasing it and clearing the carrier afterwards. Almost no system does all five. Most do one or two and rely on the body, or a clinician, for the rest.
- DNA nanostructures mostly handle targeting and release. The 2018 thrombin carrier was a sheet of DNA origami rolled into a tube with the enzyme attached inside. It was held shut by DNA “fasteners” that included an aptamer, a short DNA strand that binds a specific protein. When the aptamer met nucleolin, a protein found on tumour blood-vessel cells, the fasteners released and the tube opened. Movement came from the bloodstream. The structure didn’t steer.
- Catalytic nanomotors add their own motion. In the bladder studies from Samuel Sánchez’s group at IBEC in Barcelona, urease enzymes on the particle’s surface break down urea in urine. That reaction pushes the particles around and mixes them through the bladder. Their motion isn’t directed. They don’t steer towards a tumour, but they spread and penetrate more than passive particles do.
- Magnetic microrobots hand control to an operator. External electromagnets roll or pull the capsule through vessels, X-ray imaging tracks it, and a high-frequency magnetic field heats it to dissolve the shell and release the drug. The robot itself makes no decisions. It’s an extension of the interventional radiologist.
Clearance is the step most often left out of diagrams. DNA degrades in the body, and the 2018 study reported no obvious immune reaction in mice or pigs. Silica, iron oxide and tantalum are another matter. Where they end up, and how fast they leave, has to be measured for each design.
Four nanorobotic drug delivery studies and what they showed
These four studies were chosen because they sit at different points on the path from concept to clinic, not because they’re the only important work.
2012: logic-gated DNA barrel, in cell culture
Shawn Douglas, Ido Bachelet and George Church at Harvard’s Wyss Institute published a hexagonal DNA origami barrel in Science in 2012. It was closed by two aptamer “locks” and opened only when both locks found their target molecules on a cell surface, working like a logical AND gate. Inside, it carried antibody fragments that altered signalling in the target cells. The work showed that a DNA container could make a simple decision based on what it touched. All of it was done in cell culture. There was no bloodstream, no immune system and no question of dose.
2018: thrombin-loaded DNA nanorobot, in mice and pigs
The Li et al. study moved the same idea into animals. Injected intravenously into tumour-bearing mice, the nucleolin-triggered tube delivered thrombin to tumour blood vessels, causing clotting, tumour tissue death and slower growth. The authors reported the structures were safe and immunologically inert in mice and in Bama miniature pigs. What this doesn’t establish is just as important. The pig work assessed safety, not tumour response. Mouse tumours are small and grown to a set size. And whether thrombin, a powerful clotting enzyme, could be used without clotting healthy vessels in human cancer patients is a question that only human studies could answer.
2024: urease-powered nanobots, in mouse bladders
Cristina Simó, Samuel Sánchez and colleagues reported in Nature Nanotechnology that radio-iodinated, urease-coated mesoporous silica particles, instilled into the bladders of mice with orthotopic bladder tumours, accumulated about eight times more at the tumour on PET imaging. Treated mice showed tumour volumes about 90% smaller. The approach is clever because the bladder is a closed cavity, filled with urea that serves as fuel, and already treated by instilling drugs. But it remains a mouse study, and it delivered a radioactive payload, which brings its own dosing and safety questions.
2025: magnetic microrobots, in vessel models, pigs and a sheep
Fabian Landers, Bradley Nelson and colleagues at ETH Zurich described in Science a dissolvable gel capsule containing iron oxide for steering and tantalum for X-ray visibility. It was deployed from a modified catheter and guided with a clinical electromagnetic navigation system. According to ETH, the capsules carried a clot-dissolving agent, an antibiotic and a tumour drug in testing. They reached their intended location in more than 95% of tested cases, were navigated in pigs and in the cerebrospinal fluid of a sheep, and dissolved a clot in a silicone vessel model. This is the most clinically oriented of the four. It uses existing operating-room equipment, and it’s designed to be seen and steered. It still isn’t a treatment result. The reported therapeutic effect, the dissolved clot, was in a model, not an animal.
Read together, the studies show a familiar pattern. Each one proves a mechanism under conditions the researchers chose, which is what good early research should do. As our piece on why benchmark scores fail to predict production performance argued about AI models, success under chosen test conditions doesn’t transfer automatically to the conditions that matter.
Nanorobots for drug delivery in clinical trials: the evidence
Evidence statement, dated 17 October 2026: We found no registered, ongoing or completed human clinical trial of a nanorobotic or microrobotic drug-delivery system, and no regulatory approval of one. We couldn’t query ClinicalTrials.gov directly from our research environment. This finding rests on web searches of registry content, the peer-reviewed literature and company announcements, so it should be read as “not found”, not as “proven absent”.
Three things are easily mistaken for clinical progress.
- Company plans. Bionaut Labs, a Los Angeles start-up developing magnetically steered microscale robots, told Drug Delivery Business in 2021 that it was targeting human clinical trials by 2023, starting with chemotherapy for brainstem glioma. We found no public record that such a trial began. The ETH team says it wants to begin human trials as soon as possible, but has given no date.
- Robots of a different kind. Microbot Medical’s Liberty system received FDA 510(k) clearance in September 2025 as a single-use, remotely operated robotic system for peripheral endovascular procedures. It’s a medical robot with “microbot” in the company name. It isn’t a microrobot that delivers drugs.
- Nanoparticle trials. Registries contain many trials of liposomes, lipid nanoparticles and polymer nanoparticles. They’re valuable, but they test passive carriers, and none of them is a nanorobot trial.
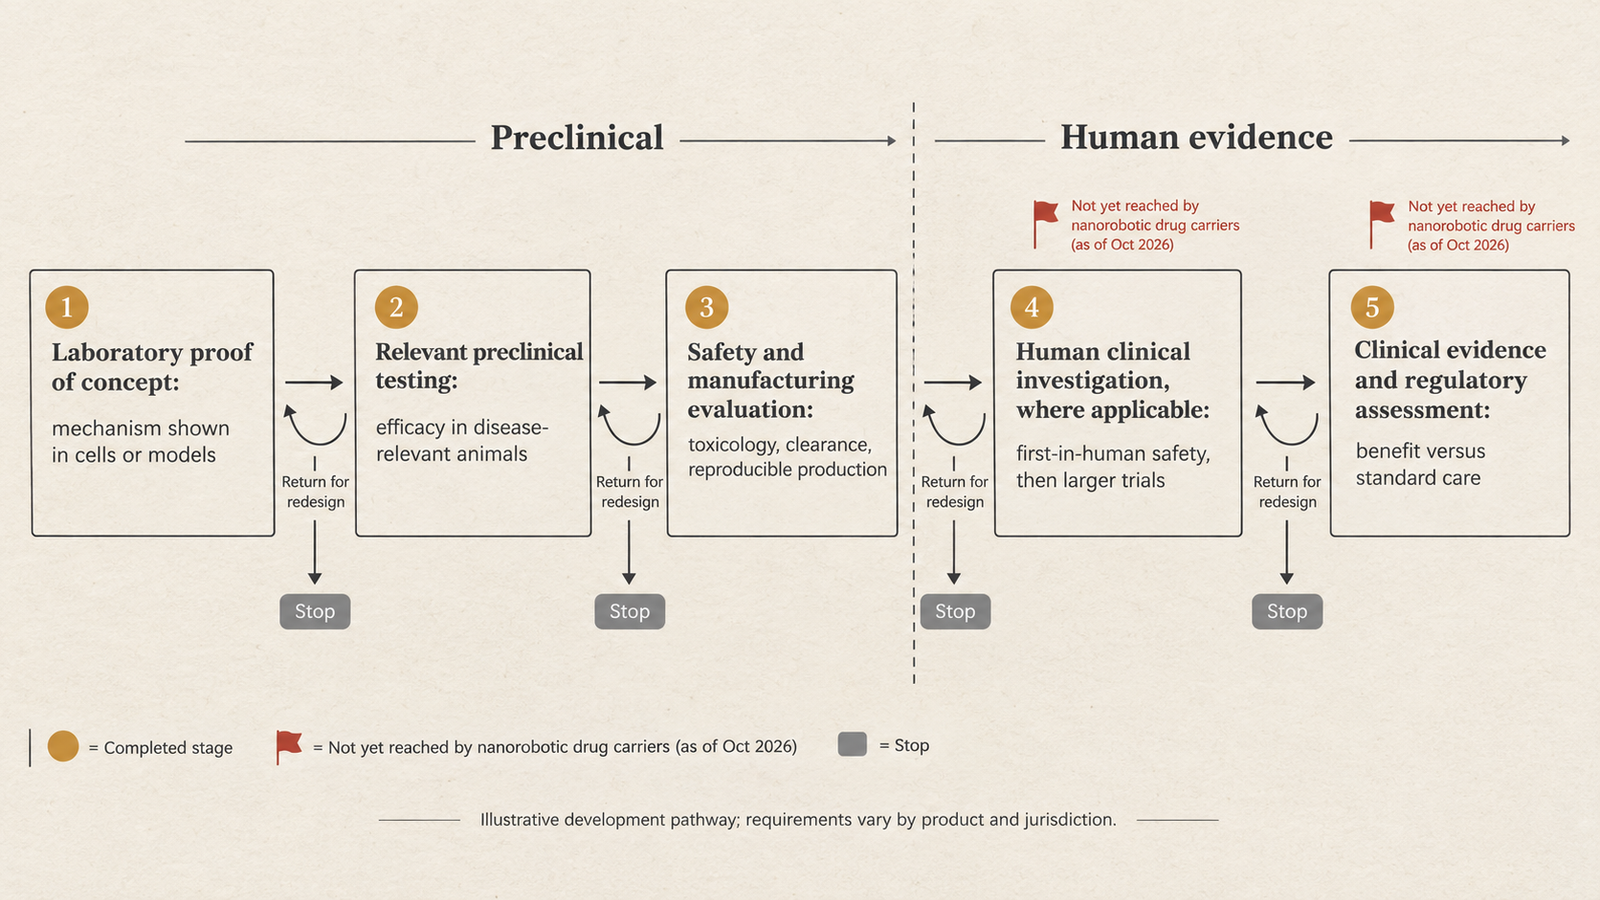
The gap is real, and it isn’t surprising. Every system above would be regulated as a new drug, a new device, or a combination of the two. Each would need a manufacturing process and a toxicology package before a first-in-human study could be approved. None has published that evidence.
The engineering problems animal studies cannot settle
Animal studies show whether something can work. Clinical use raises different questions, and the four studies above leave most of them open.
- Scale and flow. A mouse’s blood volume is a few millilitres, and its tumour sits a few millimetres from a major vessel. Human circulation is longer, faster and branches far more. The ETH team built its system around this problem, combining three navigation modes to handle different flow speeds. But it was tested in pigs and a sheep, not in diseased human vessels with plaque, clots and abnormal anatomy.
- Dose that matters clinically. Releasing a payload isn’t the same as releasing enough of it. A capsule small enough to pass through cerebral vessels carries a small drug load. The authors’ own abstract notes that the design has to balance magnetic material, contrast agent and drug capacity in the same small volume. Whether that capacity is enough for a given indication has to be shown drug by drug.
- Where the material goes. DNA is biodegradable, but its fate in the human immune system at therapeutic doses hasn’t been measured. Mesoporous silica, iron oxide and tantalum each need their own studies of distribution, accumulation and excretion. Reporting “no obvious toxicity” in a short animal study isn’t the same as a toxicology package.
- Manufacturing. DNA origami is assembled from hundreds of short strands, and making it at clinical scale, with consistent folding, purity and stability, is an unsolved industrial problem. A microrobot system adds a device to the drug: a catheter, a navigation system and imaging, each built and validated to medical-device standards.
- Cost and comparison. A new system has to beat what’s already used: intravesical chemotherapy for bladder cancer, catheter-directed thrombolysis for clots, convection-enhanced delivery for brain tumours. It needs a clear advantage in outcome, safety or practicality to justify its complexity.
What a credible path to clinical use looks like
There is no shortcut through the regulatory sequence, and each step tests something the previous one couldn’t.
- Preclinical efficacy in relevant models. This means disease models that resemble the human condition, ideally in more than one species, with doses that could translate to people.
- Formal toxicology and pharmacology. These are GLP-compliant studies of distribution, accumulation, immune response and clearance of every component, including the carrier, not just the drug.
- Manufacturing and quality control. A reproducible process with defined specifications, sterility and stability, documented to the standard regulators expect for a clinical product.
- First-in-human study. Usually a small safety study in patients with limited options, in which the system and its control setup are used as the regulator approved.
- Larger trials and regulatory assessment. Evidence that the system improves outcomes compared with standard care, not just that it’s safe.
Passing one step doesn’t predict the next. Many nanomedicines have looked strong in mice and failed in people. A first-in-human study that shows safety under tightly controlled conditions won’t establish efficacy either. That’s the same limit we described in why a passing red-team test doesn’t prove an AI system is safe: a result applies to the configuration that was tested.
Where nanorobotic drug delivery could make a difference
The most plausible early uses share a feature. They involve a cavity or vessel a clinician can already reach, an existing procedure that the robot could improve, and a drug whose benefit is limited by poor local concentration.
- Bladder cancer. Bladder drugs are already instilled directly, and the urine provides the fuel for urease motors. The 2024 study’s eightfold tumour accumulation suggests that enzyme-driven mixing could improve on passive instillation. What’s still needed is evidence in larger animals, a non-radioactive or clinically established payload, and a direct comparison with current intravesical therapy.
- Stroke and blood clots. Magnetically guided capsules carrying a clot-dissolving drug could, in principle, deliver a concentrated dose to an occlusion. That could reduce the systemic bleeding risk of intravenous thrombolysis. The ETH work shows navigation in pigs and clot dissolution in a model. It doesn’t yet show outcomes in an animal stroke model, let alone in patients, where minutes matter and catheter procedures already exist.
- Brain tumours. Steering through cerebrospinal fluid, as shown in a sheep, could in principle reach brain regions that systemic drugs struggle to penetrate. No human evidence has been published.
The next milestone worth watching
The milestone that would change the assessment most is a registered first-in-human study of a nanorobotic or microrobotic drug-delivery system, with its manufacturing and toxicology documented. Magnetic microrobots look closest, because they use clinically familiar components and show up on standard imaging. Enzyme-driven particles in the bladder are a reasonable second, because the delivery route already exists. Until a trial like that is registered with a defined intervention and endpoints, claims that nanorobots are “entering the clinic” have nothing to point to.
What the evidence lets us say
The evidence supports a narrower claim than the headlines usually make. Researchers have built nanoscale and microscale systems that open on contact with a target, propel themselves through biological fluids, or can be steered with magnets to a chosen point in an animal’s vasculature. Those results are real and peer-reviewed.
The evidence doesn’t support saying that nanorobots for drug delivery have been tested in patients, that any is close to approval, or that animal tumour responses predict human ones. Between the demonstration and the patient lie manufacturing, dose, clearance and a regulatory process that none of these systems has publicly entered. A mouse tumour shrinking by 90% is a finding about a mouse.
Frequently asked questions
What are nanorobots for drug delivery?
They’re nanoscale or microscale systems that carry a drug and sense, move or are controlled in ways passive carriers can’t. Examples include DNA structures that open on contact with a tumour marker, enzyme-powered particles and magnetically steered capsules. The term is used loosely.
Are nanorobots currently used to deliver drugs to human patients?
Not as far as we could verify. As of 17 October 2026, we found no registered or completed human trial of a nanorobotic or microrobotic drug-delivery system, and no approved product. The published work so far is in cells, animals or physical models.
What is the difference between a nanorobot and a nanoparticle?
A conventional nanoparticle, such as a liposome or lipid nanoparticle, carries a drug passively and goes where blood flow and chemistry take it. A nanorobot adds a controlled function: it propels itself, responds to a specific trigger, or is steered externally. Several nanoparticle medicines are approved; no nanorobot is.
How do nanorobots navigate through the body?
Most don’t steer. DNA nanostructures travel with the blood and act when they bind a target. Enzyme-powered particles move but don’t aim. Magnetic microrobots are steered by external electromagnets under X-ray guidance, with a clinician in control.
What safety and manufacturing challenges remain?
The main ones are the long-term fate of materials such as silica and iron oxide, immune responses to DNA structures at clinical doses, delivering enough drug to matter, and reproducible manufacturing at scale. None of the leading systems has published a full toxicology or manufacturing package.
When could nanorobotic drug delivery become clinically available?
No credible date can be given. A first-in-human safety study would be the first concrete step, and none has been verified. Larger trials and regulatory review would follow over years, and many candidates fail.